
PHARMACOLOGY / FREE MEDICATION REFERENCE
Common medications.
What matters during PT.
Drug names are easier to remember when you know why they matter in the clinic. Start with the groups below: what you may notice, what to check, and when to bring in the clinical team.
Take the reference with you
Download the free medication reference · 3-page PDF ↗
12 medication groups, common generic names, PT considerations, and selected interactions. Based on our original autonomic nervous system and blood pressure medication lists, with linked current drug labels. No signup required.
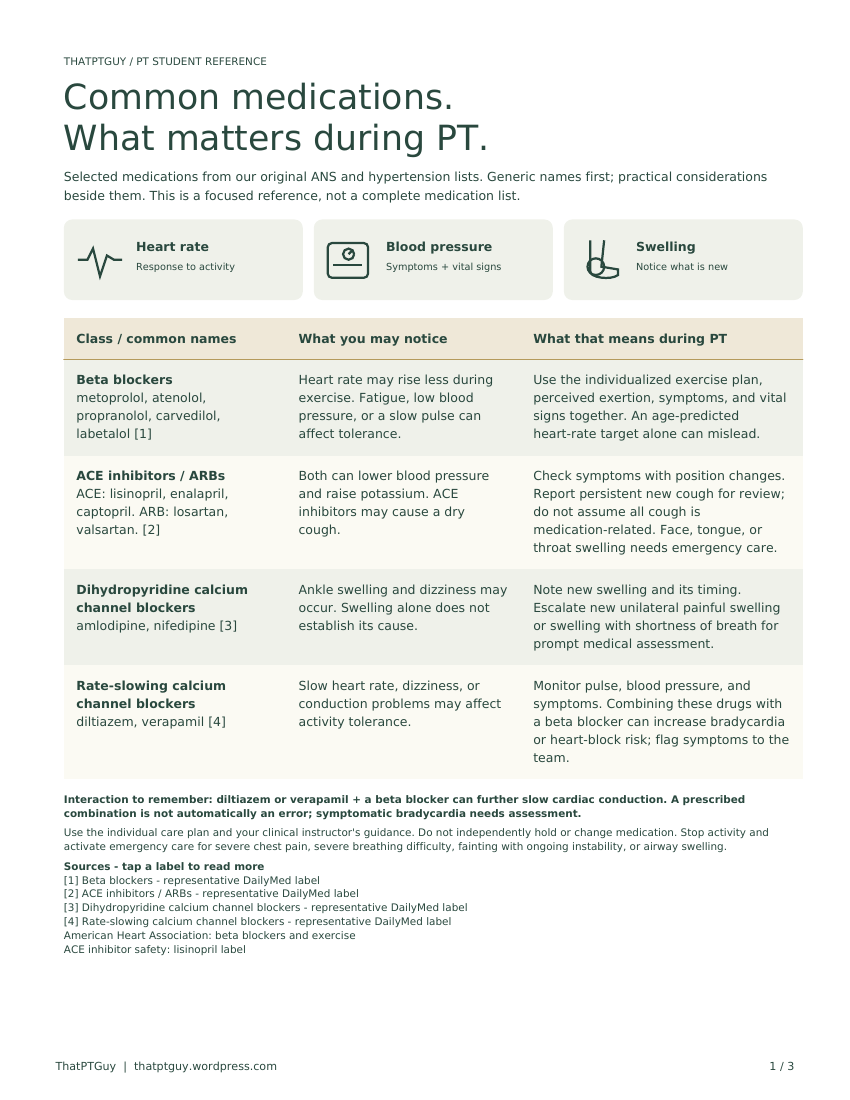
Preview the printable guide
Choose one group to start
Pick a medication from your notes or clinical placement. Find its group, then connect one possible effect to a specific thing you would check during PT. You do not need to learn every row in one sitting.
Heart rate and exercise
Beta blockers
Common names: metoprolol, atenolol, propranolol, carvedilol, labetalol
What you may notice: Heart rate may rise less during exercise. Fatigue, low blood pressure, or a slow pulse can affect tolerance.
During PT: Use the individualized exercise plan, perceived exertion, symptoms, and vital signs together. An age-predicted heart-rate target alone can mislead.
ACE inhibitors / ARBs
Common names: ACE: lisinopril, enalapril, captopril. ARB: losartan, valsartan.
What you may notice: Both can lower blood pressure and raise potassium. ACE inhibitors may cause a dry cough.
During PT: Check symptoms with position changes. Report persistent new cough for review; do not assume all cough is medication-related. Face, tongue, or throat swelling needs emergency care.
Dihydropyridine calcium channel blockers
Common names: amlodipine, nifedipine
What you may notice: Ankle swelling and dizziness may occur. Swelling alone does not establish its cause.
During PT: Note new swelling and its timing. Escalate new unilateral painful swelling or swelling with shortness of breath for prompt medical assessment.
Rate-slowing calcium channel blockers
Common names: diltiazem, verapamil
What you may notice: Slow heart rate, dizziness, or conduction problems may affect activity tolerance.
During PT: Monitor pulse, blood pressure, and symptoms. Combining these drugs with a beta blocker can increase bradycardia or heart-block risk; flag symptoms to the team.
Interaction to remember: diltiazem or verapamil + a beta blocker can further slow cardiac conduction. A prescribed combination is not automatically an error; symptomatic bradycardia needs assessment.
Fluids, blood pressure, and standing
Loop / thiazide diuretics
Common names: Loop: furosemide, bumetanide. Thiazide-type: hydrochlorothiazide, chlorthalidone.
What you may notice: More urination; volume depletion, low blood pressure, and electrolyte disturbances are possible.
During PT: Plan bathroom access. New cramps, unusual weakness, dizziness, or palpitations merit assessment. Follow the patient's fluid plan; do not automatically recommend extra fluids.
Potassium-sparing diuretics
Common names: spironolactone, eplerenone, triamterene
What you may notice: Potassium can become too high, particularly with kidney impairment or other potassium-raising drugs. Symptoms may be absent.
During PT: Review available labs and the care plan. Flag ACE inhibitor/ARB plus potassium-sparing therapy for medication review when concerns arise. Do not recommend potassium supplements or salt substitutes.
Alpha-1 blockers
Common names: doxazosin, terazosin, tamsulosin
What you may notice: Dizziness with standing or fainting can occur. Tamsulosin is often used for urinary symptoms, but orthostasis still matters.
During PT: Use gradual transitions and appropriate guarding. If dizziness occurs, stop the task, position safely, assess vital signs, and follow the clinical escalation plan.
Midodrine
Common names: midodrine
What you may notice: Used for symptomatic orthostatic hypotension; it can also cause high blood pressure while lying flat.
During PT: Check the prescribed blood-pressure and positioning plan before prolonged supine treatment. Monitor symptoms and blood pressure; do not independently change dose timing.
Classification check: spironolactone and eplerenone block aldosterone receptors. Triamterene is potassium-sparing through a different mechanism. Loop/thiazide drugs can lower potassium; potassium-sparing drugs can raise it.
Alertness, balance, and breathing
Clonidine
Common names: clonidine
What you may notice: Drowsiness, dizziness, and a slower pulse may affect participation. Abrupt withdrawal can cause rebound hypertension.
During PT: Check alertness and vital signs before challenging balance or exertion. If doses were missed and blood pressure or symptoms are concerning, contact the clinical team; do not advise abrupt stopping.
Tizanidine
Common names: tizanidine
What you may notice: A muscle relaxant that can cause sedation, weakness, and low blood pressure. Other sedating drugs can add to impairment.
During PT: Check transfer safety and alertness. Tizanidine with ciprofloxacin or fluvoxamine is contraindicated: flag the combination promptly to the pharmacist/prescriber.
Systemic antimuscarinics
Common names: oxybutynin, tolterodine, benztropine
What you may notice: Dry mouth, blurred vision, and confusion may affect safety. Oxybutynin can reduce sweating and increase overheating risk.
During PT: Consider vision and cognition during mobility tasks. For oxybutynin, avoid excessive heat and watch for heat intolerance. Effects vary by drug and route; inhaled agents are not equivalent.
Inhaled short-acting beta-2 agonist
Common names: albuterol
What you may notice: Used for bronchospasm. Tremor, palpitations, or a faster heart rate can occur.
During PT: Ask about recent inhaler use when interpreting symptoms and heart rate. Follow the prescribed rescue plan. Worsening breathing after use or poor relief requires escalation.
Interaction to remember: tizanidine + ciprofloxacin or fluvoxamine is contraindicated. Sedation and hypotension are not just study facts when a patient is transferring or walking.
Watch one example
Watch my beta-blocker exercise Short ↗
Why might an age-predicted target heart rate be less useful for someone taking a beta blocker? Use the reference to explain what else you would monitor. The American Heart Association explains how beta blockers affect exercise.
Need the foundations first?
My pharmacokinetics vs. pharmacodynamics Short ↗
My ADME Short ↗
Before you use this in clinic
A medication is one possible contributor to a symptom, not proof of its cause. Verify the actual product, complete medication list, baseline, available labs, and individual care plan with your clinical instructor. These PT considerations are educational applications of the linked labeling; the list is selective and does not include every adverse effect or interaction.
Do not independently hold or change medication. Stop activity and activate emergency care for severe chest pain, severe breathing difficulty, fainting with ongoing instability, or face/tongue/throat swelling. Follow your setting’s monitoring and escalation protocols.
Sources checked October 26, 2026. Additional ACE inhibitor safety source: lisinopril prescribing information ↗. Each group links to a representative drug label; check the label for the patient’s specific medicine.
What medication should we add next?
Tell us the drug or class and the PT question you want answered. Comments are public; leave out patient details and protected course or exam questions. New commenters may need approval.


Leave a Reply