
FROM MY PT SCHOOL NOTES · NEUROLOGY · UNIT 3 · CHAPTER 10
How do stroke location and vascular territory affect function?
The vascular territory helps explain what a person may have difficulty doing. The useful PT question is not ‘Can I diagnose the artery?’ but ‘What impairments, safety problems and participation barriers should I assess?’
Build the clinical picture
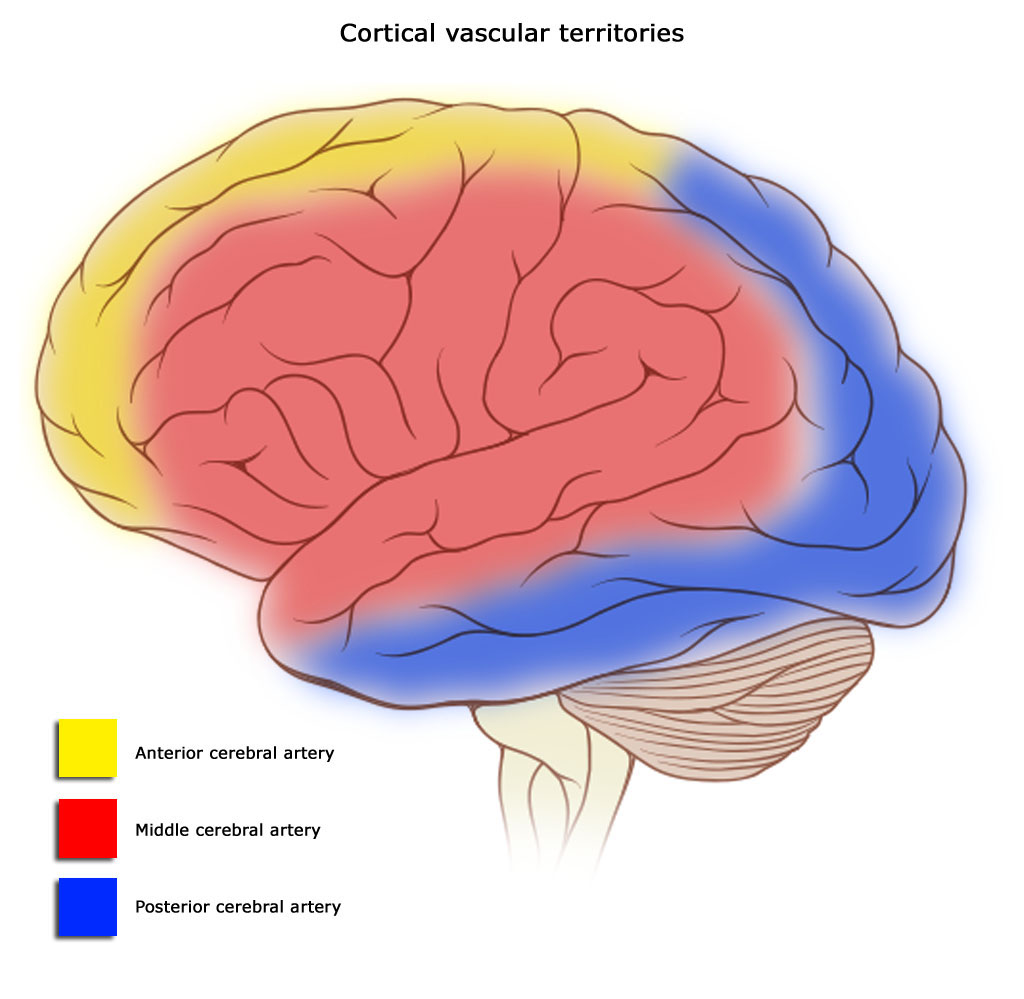
Understand the broad vascular map
Anterior cerebral artery (ACA) involvement often affects medial frontal/parietal regions and may produce contralateral leg-predominant weakness or sensory changes, with alterations in initiation or behavior. Middle cerebral artery (MCA) involvement commonly affects lateral hemispheric networks and may produce opposite-side face/arm deficits, language problems in the dominant hemisphere, or attention/visuospatial deficits in the nondominant hemisphere.
Posterior cerebral artery (PCA) involvement may produce visual-field deficits, memory changes or thalamic sensory findings depending on branches. Vertebrobasilar stroke can involve brainstem and cerebellar systems, affecting gaze, balance, swallowing, coordination, cranial nerve function and vital neural processes.
Some impairments sound similar but are different
Aphasia is impaired language formulation or comprehension; dysarthria is a speech motor-production impairment. Hemianopia refers to visual-field loss; hemispatial neglect involves reduced awareness/attention toward part of space and can coexist with field loss. Apraxia affects skilled learned action beyond basic strength alone.
When language or cognition affects consent, education or safety, adapt the interaction and involve appropriate communication specialists. A person who cannot name an object may still understand the instruction; do not equate all aphasia with global cognitive loss.
Never over-localize
Vascular anatomy varies; smaller perforating lesions, multiple lesions, edema, cortical/subcortical networks and medical complications alter presentations. A ‘classic’ territory pattern is a learning aid, not an automatic diagnosis. An abrupt deficit of any territory still calls for urgent stroke evaluation.
At a glance
| ACA | Often leg-predominant motor/sensory changes; assess mobility, initiation and cognition |
| MCA | Often face/arm motor changes and language or spatial-attention problems |
| PCA | Often visual-field, memory or selected thalamic sensory effects |
| Vertebrobasilar | May affect eye movements, coordination, swallowing, gait or consciousness |
PT clinical connection
Use the suspected lesion distribution to select hypotheses: test limb function and transfers, visual-field concerns, attention during gait, communication ability and task performance. Prioritize observed function and the established medical diagnosis over expected textbook patterns.
Apply it to a patient
A person after right hemispheric stroke repeatedly misses the left side of doorways. Does this prove they have left visual-field loss?
Reasoning: No. Visual-field loss and spatial neglect can produce superficially similar navigation issues. They require different targeted assessments and often collaboration with OT, vision and neurology professionals.
Check your understanding
What would you test differently when a patient has contralateral leg-predominant weakness versus diplopia with limb ataxia?
Original class-note sources: 1 Intro to Stroke.pdf; 2 Diagnosis and Treatment of the Stroke Patient.pdf; 4 Rehabilitation.pdf. Study note: These territory descriptions are broad patterns. Compare your original lectures with contemporary neuroanatomy and the patient’s actual medical and functional findings. Independently organized educational material, not an acute-care protocol or replacement for professional training.


