
FROM MY PT SCHOOL NOTES · CARDIOPULMONARY · CHAPTER 8
Can a Patient With Oxygen, Lines or a Ventilator Mobilize?
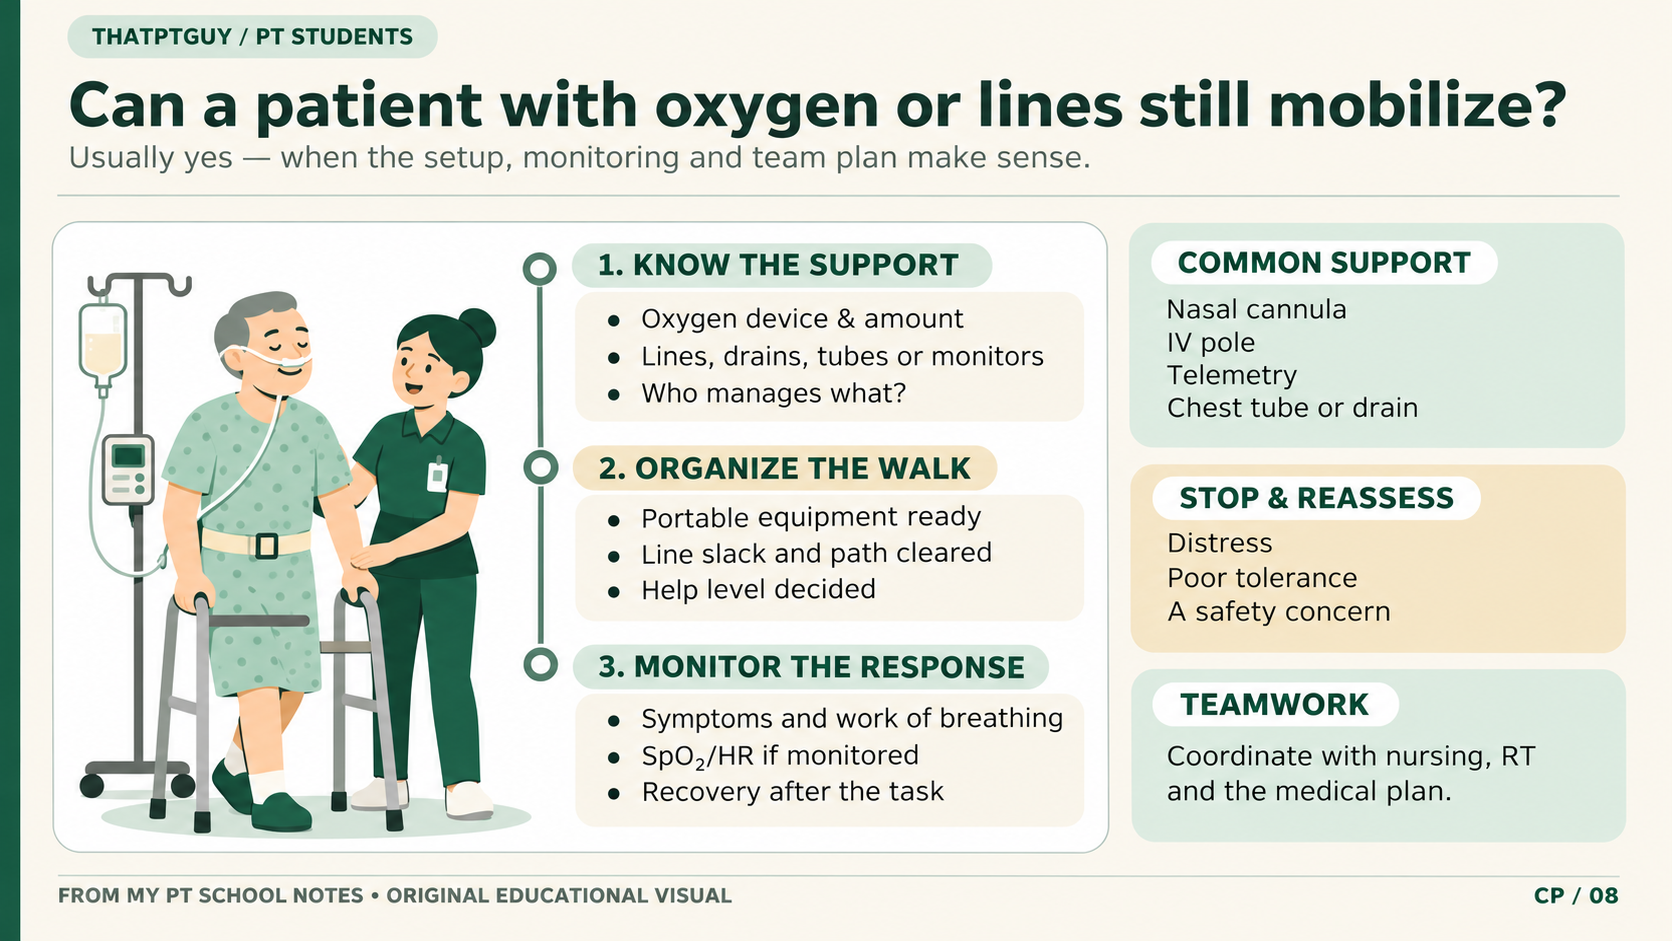
A line or a ventilator is not a yes/no answer to mobility. The decision depends on clinical stability, equipment, staff and the person’s participation.
1. Start with the person and the planned task
Assess symptoms, alertness, recent trends, cardiopulmonary status and the intended activity. Respiratory support and monitors provide information, but no single displayed number makes movement automatically safe.
The SCCM ICU Liberation framework includes early mobility and exercise as part of an interprofessional approach. Each mobility goal is adapted to neurologic, cardiac, pulmonary, line/drain and staffing needs.
Does having a ventilator always prohibit all movement?
Reasoning: No. Some carefully assessed patients can mobilize with specialized staff and equipment, while others are too unstable.
2. Know what equipment does—not just its name
Pulse oximeters estimate oxygen saturation; arterial lines measure continuous invasive pressure; central lines provide vascular access; chest tubes manage pleural drainage. Ventilatory support and oxygen devices introduce additional monitoring and coordination needs.
Before movement, confirm device securement, available slack, portable support and who is responsible for each line. Do not independently disconnect oxygen, change ventilator settings, clamp drains or alter infusions.
If the walk is only a few steps, can you temporarily remove oxygen without checking?
Reasoning: No. Confirm the prescription and arrange an appropriate mobility setup with the responsible clinicians.
3. Interpret oxygen and monitor information in context
A nasal cannula and high-flow device do not provide interchangeable respiratory support. A flow number is not always a fixed FiO2. Pulse-ox measurements can be affected by motion or perfusion, so trends and symptoms matter.
Patient-specific oxygen goals and support orders must come from the clinical plan. PTs can observe and communicate response without inventing universal ‘clearance’ cutoffs.
Would a stable SpO2 reading rule out other reasons to stop a walk?
Reasoning: No. Symptoms, hemodynamics, lines, fatigue and clinical change can still make an activity inappropriate.
Apply it to a clinical situation
Scenario: A patient has a pleural drain, nasal oxygen and IV lines. The team would like to try a hallway walk.
What is the stronger reasoning?
Reasoning: Identify the clinical stability, tubing and drainage requirements, necessary portable equipment, assigned staff and patient goals before moving. Continue observing the patient, monitor and lines together.
Common trap: Treating a device as either an automatic prohibition or an irrelevant inconvenience.
Sources & learning scope
Based on “13 Equipment student.pdf” and the acute-care lectures, updated with SCCM ICU Liberation and AARC oxygen-care guidance. No fixed physiologic cutoff is presented as universal. This independent teaching summary is based on the author’s PT school notes; it is not a clinical protocol, certification or official exam guide.

